



The short answer
Which symptoms should you discuss with a clinician
Tell your clinician about new or worsening back pain, pain that disturbs sleep, tenderness in a particular area, or symptoms extending into a leg. If you have or previously had cancer, do not assume new back pain is simply a repeat of an earlier problem. If you have a cancer history and develop this kind of concerning pain, contact your healthcare team the same day. [1]
These warning signs are not a tumor checklist. A systematic review of “red flags” for spinal malignancy found that a single warning sign is not sufficient to establish a diagnosis. A history of cancer is important, while many other individual findings can produce false alarms. Nighttime pain does not prove that a tumor is present; its absence does not rule out a serious cause either. [2]
Why can a spinal tumor resemble a herniated disc
A herniated disc and certain tumors around the spine can affect nerve structures and produce similar complaints. Saying that pain “shoots down my leg” helps describe the symptom, but does not identify its cause. Likewise, a previous diagnosis of a herniated disc does not remove the need to assess new or substantially changed symptoms. Back-pain guidelines recommend considering alternative causes, particularly when symptoms change. [5]
Symptom or situation | What it can and cannot tell you | What matters during assessment |
|---|---|---|
Pain traveling down a leg or numbness | Can accompany nerve involvement; does not identify the cause by itself. | The pattern, examination and changes over time are considered together. |
Nighttime pain or pain at rest | May warrant attention; does not establish a tumor diagnosis. | Cancer history and other symptoms provide context. |
A previous herniated-disc diagnosis | Does not automatically explain new complaints. | The clinician checks whether previous findings fit the current symptoms. |
New bladder or bowel problems, or numbness around the groin | Can have different causes, including a herniated disc. | Emergency assessment is needed, rather than self-diagnosis. |
This comparison is intended to help you describe changes at a consultation, not to diagnose yourself. [1], [2], [3], [5]
When should you seek emergency help
What do an examination and MRI show
Your clinician asks about the course of the pain, associated symptoms and previous illnesses. Examination and imaging provide different parts of the assessment: a change visible on a scan must be considered alongside the symptoms it may or may not explain. A single word in an MRI report is not enough to make a treatment decision. [5]
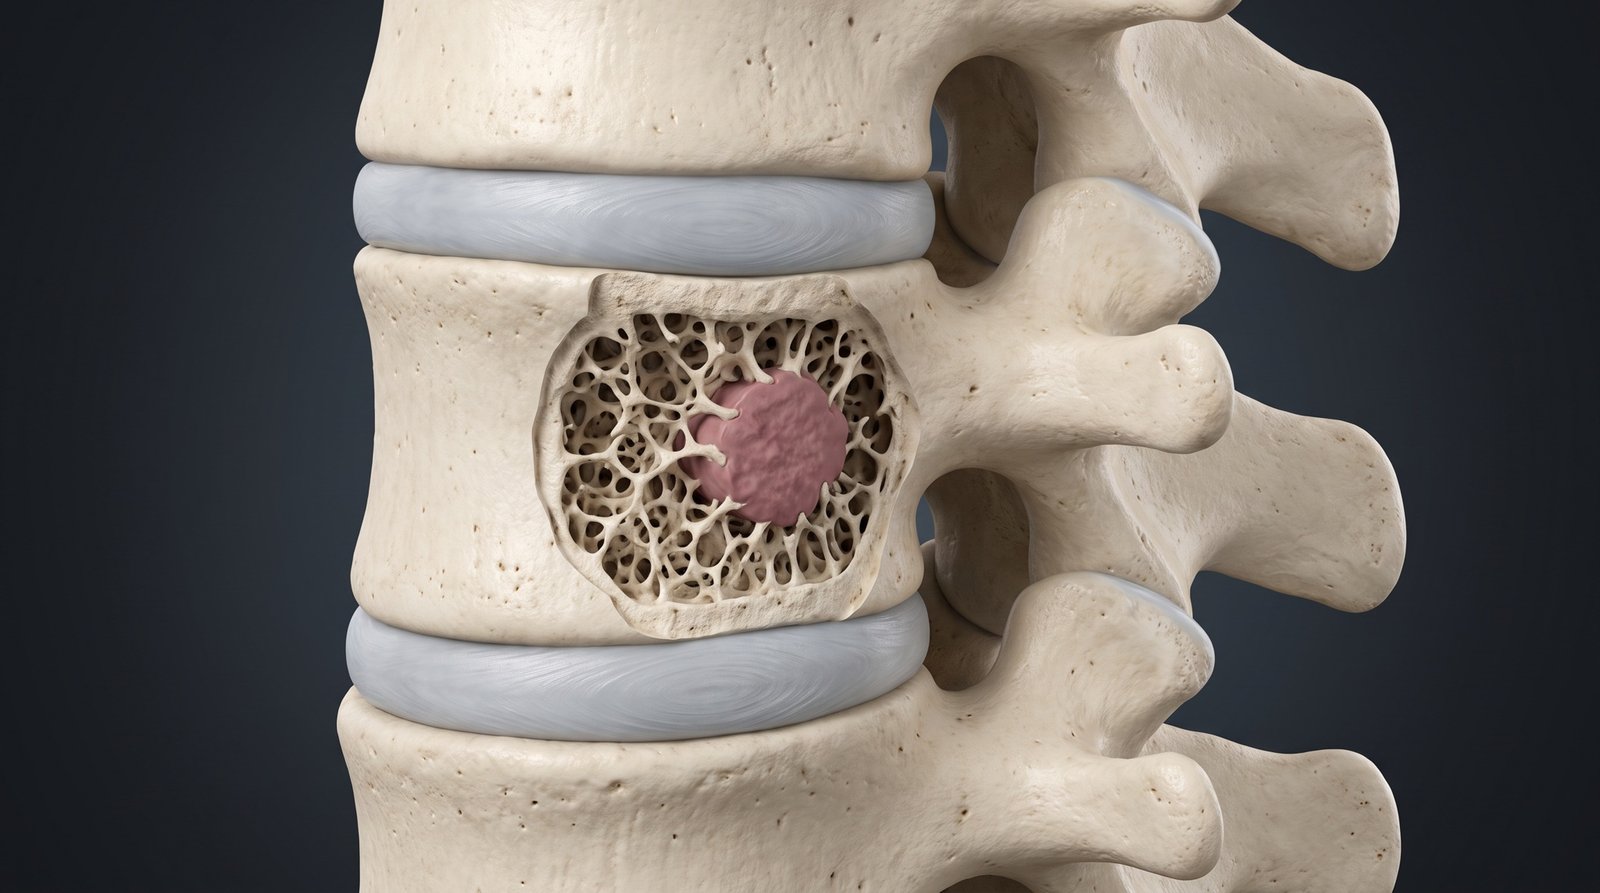
MRI helps assess where a suspected tumor is located and how it relates to nerve structures. If a tumor inside the spinal cord is suspected, the imaging assessment is planned accordingly. Definitive classification may require pathological and molecular examination. The same sequence of tests is not appropriate for every mass. [4]
Not everyone with back pain needs an immediate MRI. When a serious cause is not suspected, imaging is selected according to whether the result is likely to change management. Neither “everyone needs an MRI” nor “back pain never needs an MRI” is a reliable rule. The clinical circumstances determine the next step. [5]
Does finding a tumor always mean surgery
Treatment is not selected from the tumor's name alone. In metastatic spinal disease, the team considers nerve compression, the tumor's response to different treatments, the spine's mechanical stability and the person's overall health. Radiation, surgery and systemic cancer treatments may have different roles or be used together. A recommendation for one person may not suit another. [6]
For a different tumor group, such as an ependymoma arising within the spinal cord, surgery and additional treatment are considered within a different clinical framework. Recommendations for spinal metastases should therefore not be applied to all spinal cord tumors. Individual plans are developed through assessment by the relevant specialists. [4]
How can you prepare for a consultation
Gather previous scan images as well as reports, any pathology results and a list of medications. A short symptom history can also help:
1. When did the pain begin, and how does it differ from previous pain?
2. Is there numbness or weakness, and how does it affect daily activities?
3. Have you had a cancer diagnosis or previous treatment?
4. Which symptoms appeared later, and when did they change?
Before leaving, clarify the next step and ask which changes should prompt you to seek help sooner. Do not delay emergency care to complete this preparation.
Frequently asked questions 6 short answers
Is pain always the first symptom of a spinal tumor
Does back pain at night mean I have a tumor
Does a herniated-disc diagnosis rule out a tumor
An existing diagnosis does not necessarily explain all later symptoms. If symptoms change or follow an unexpected course, your clinician considers alternative causes again. [5]
Can serious nerve compression occur without a cancer history
Yes. New bladder or bowel dysfunction or numbness around the groin can occur for different reasons, including a herniated disc. These symptoms need emergency assessment even without a history of cancer. [3]
Can an MRI report confirm the exact tumor type
MRI helps assess location and the likely cause. Particularly for tumors within the spinal cord, definitive classification may require tissue and molecular examination. The next step is individualized. [4]
How is spinal tumor treatment chosen
The tumor's origin and location matter. For metastatic disease, clinicians consider nerve compression, spinal stability, tumor characteristics and overall health together. There is no single treatment for every patient. [6]
References
1. NICE. Spinal metastases and metastatic spinal cord compression. NG234, 2023. Particularly sections 1.3 and 1.5. Official guideline. No DOI or PMID assigned to this guideline.
2. Henschke N, Maher CG, Ostelo RWJG, et al. Red flags to screen for malignancy in patients with low-back pain. Cochrane Database Syst Rev. 2013;(2):CD008686. DOI: 10.1002/14651858.CD008686.pub2. PMID: 23450586.
3. NICE. Suspected neurological conditions: recognition and referral. NG127. Cauda equina and neurological referral recommendations. Official guideline. No DOI or PMID assigned.
4. Rudà R, Reifenberger G, Frappaz D, et al. EANO guidelines for the diagnosis and treatment of ependymal tumors. Neuro Oncol. 2018;20(4):445–456. DOI: 10.1093/neuonc/nox166. PMID: 29194500.
5. NICE. Low back pain and sciatica in over 16s: assessment and management. NG59. 2016; updated 2020. Particularly recommendations 1.1.1 and 1.1.4–1.1.6. Official guideline. No DOI or PMID assigned.
6. Laufer I, Rubin DG, Lis E, et al. The NOMS framework: approach to the treatment of spinal metastatic tumors. Oncologist. 2013;18(6):744–751. DOI: 10.1634/theoncologist.2012-0293. PMID: 23709750.